
Published: 15 October 2026
Medically reviewed by Dr. Pranay Shah, MS (ObGy), Director & Chief Fertility Consultant, Wellspring IVF & Women’s Hospital, Ahmedabad
Last medically reviewed: 15 October 2026
No. For couples without a male factor, injecting sperm directly into the egg has not been shown to produce more babies than conventional insemination in the laboratory. Randomised trials, a 2026 systematic review, a large national registry and current guidance from NICE and ASRM all reach the same conclusion. ICSI solves a fertilisation problem. Where there is no fertilisation problem, it has nothing to solve.
Intracytoplasmic sperm injection is one of the genuine breakthroughs of reproductive medicine. It made biological fatherhood possible for men whose sperm could never have fertilised an egg unaided. That success has produced an odd consequence: in many laboratories it is now used for almost every cycle, including cycles where the semen analysis is entirely normal. This article examines what happens to outcomes when ICSI is used in couples who do not need it, and why the practice persists despite the evidence.
What ICSI Changes, and What It Does Not
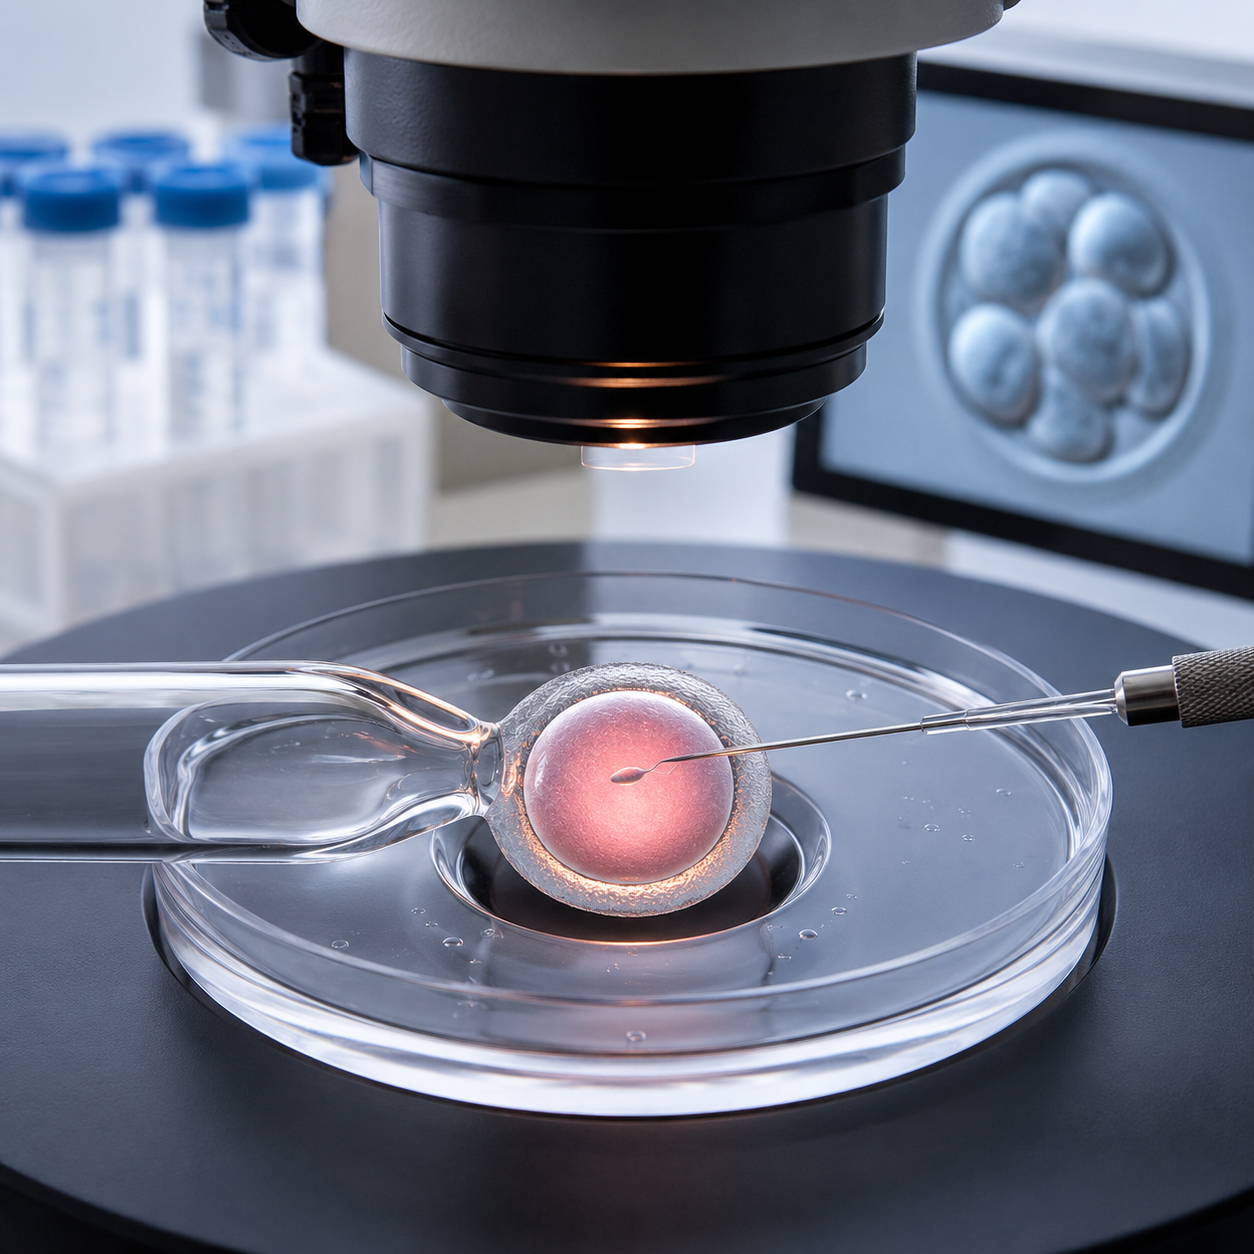
In conventional insemination during in vitro fertilisation, each egg is placed in a droplet with a prepared population of motile sperm and fertilisation occurs by the sperm’s own binding and penetration. In ICSI, an embryologist selects a single sperm and injects it through the egg’s outer layer directly into the cytoplasm. The technique therefore bypasses every step that depends on sperm number, movement and binding capacity.
That is the whole of what it does. ICSI does not improve the genetic content of the sperm, the developmental competence of the egg, the chromosomal normality of the resulting embryo, or the receptivity of the endometrium. It controls the fertilisation step and nothing downstream of it. This is why the distinction between a fertilisation outcome and a live birth outcome runs through every study discussed below, and why a technique can raise the first without moving the second.
Is ICSI Worth Doing If There Is No Male Factor?
Current guidance says no, and unusually for a contested area, the major bodies agree with each other.
NICE guideline NG257, published on 31 March 2026 and updating and replacing CG156, sets out three recommendations on the technique. Recommendation 1.50.1 says to offer ICSI using surgically retrieved sperm or frozen–thawed oocytes. Recommendation 1.50.2 says to consider ICSI where the partner with male reproductive organs has abnormal semen parameters, taking severity into account, or where a previous IVF cycle resulted in failed fertilisation or a very low fertilisation rate. Recommendation 1.50.3 is unambiguous: “Do not use ICSI for non-male factor fertility problems if the semen parameters are normal.”
The American Society for Reproductive Medicine reached the same position in its 2026 committee opinion Intracytoplasmic sperm injection for nonmale factor indications (Fertility and Sterility 2026;126:49–56), which states that “in cases without male factor infertility or a history of prior fertilization failure, the routine use of ICSI for all oocytes does not improve live birth rates”.
Does ICSI Increase Live Birth Rates in Unexplained Infertility?
It increases fertilisation in some studies, and it does not increase live births. ASRM addresses this indication directly: “ICSI for unexplained infertility without male factor infertility has been associated with increased fertilization rates in some studies. However, it has not been shown to improve live birth outcomes.”
The randomised evidence supports that. A systematic review and meta-analysis published in Human Reproduction in 2026 pooled six randomised controlled trials in couples without severe male factor infertility — a population that included non-male factor, unexplained, tubal factor and endometriosis-associated infertility, low oocyte number and non-severe male factor. Across 1,438 couples analysed for live birth, the rates were 32.8% with ICSI and 34.5% with conventional IVF, giving a pooled risk ratio of 0.96 (95% CI 0.85–1.09). Fertilisation rate showed no significant difference either. The authors concluded that the analysis “shows no advantage of ICSI over cIVF in improving live birth or cumulative live birth rates among couples without severe male factor infertility”.
The Cochrane review of ICSI versus conventional IVF where the male partner has normal total sperm count and motility (Cutting, Horta, Dang, van Rumste and Mol; updated 15 August 2023) is more cautious in its wording and identical in its direction. It found that neither method was superior for live birth, that adverse events including multiple pregnancy, ectopic pregnancy, pre-eclampsia and prematurity showed probably little or no difference, and that clinical pregnancy and miscarriage rates also showed probably little or no difference. Certainty of evidence for live birth was rated low, and for viable intrauterine pregnancy moderate.
ASRM extends the same conclusion to three indications where ICSI is often used pre-emptively: “ICSI for low oocyte yield, diminished ovarian reserve, and advanced maternal age does not improve fertilization or live birth outcomes”, and, on genetic testing, “in the absence of male factor infertility, the use of ICSI for PGT-A does not improve live birth rates, euploidy rates, or numbers of embryos”.
Evidence Check: Claim Versus Evidence
Claim | What the evidence shows | Source |
|---|---|---|
“ICSI gives everyone a better chance.” | Not supported. No advantage in live birth over conventional IVF in couples without severe male factor: 32.8% vs 34.5%, RR 0.96 (95% CI 0.85–1.09). | Systematic review of 6 RCTs, Human Reproduction, 2026 |
“ICSI is safer because it guarantees fertilisation.” | It reduces the risk of complete fertilisation failure but does not guarantee fertilisation, and in normal-semen couples it does not raise the fertilisation rate. | Human Reproduction, 2026; ASRM, 2026 |
“If the diagnosis is unexplained infertility, ICSI is the logical next step.” | Fertilisation rates rise in some studies; live birth does not. | ASRM committee opinion, 2026 |
“With few eggs, ICSI protects the cycle.” | ICSI for low oocyte yield, diminished ovarian reserve and advanced maternal age does not improve fertilisation or live birth. | ASRM committee opinion, 2026 |
“You must have ICSI if you are having genetic testing.” | Without male factor, ICSI for PGT-A does not improve live birth, euploidy rates or embryo numbers. | ASRM committee opinion, 2026 |
“ICSI is riskier for the pregnancy.” | Multiple pregnancy, ectopic pregnancy, pre-eclampsia and prematurity showed probably little or no difference between techniques. | Cochrane review CD001301, 2023 |
“Everyone uses ICSI, so it must be better.” | Utilisation greatly exceeds male-factor prevalence. In one national registry, 74.9% of retrieval cycles in patients without a male factor diagnosis used ICSI. | CARTR Plus registry study, 2026 |
What the Largest Real-World Dataset Shows
Randomised trials answer the question under controlled conditions. Registry data answer a different and equally important question: what happens when a whole country does this for a decade.
A 2026 analysis of the Canadian CARTR Plus registry examined 140,252 retrieval cycles performed between 2013 and 2022 in patients with no male factor infertility diagnosis. Of those cycles, 105,001 — 74.9% — used ICSI, and 35,251 used conventional IVF. Cumulative live birth rates were 38.5% with conventional IVF and 36.3% with ICSI (p < 0.001). The authors concluded that “in non–male factor infertility, ICSI does not improve cumulative live birth outcomes compared with conventional IVF”.
Two cautions belong with that figure. It is a descriptive registry analysis, not a randomised comparison, so the small difference in favour of conventional IVF may reflect differences between the patients selected for each technique rather than the technique itself. And it is Canadian; no equivalent national figure for ICSI utilisation has been published for India, so it should not be read as a description of Indian practice. What it does establish, robustly, is that a very large body of real-world non-male-factor cycles performed with ICSI produced no better cumulative outcome than those performed without it.
Why Do Some Clinics Use ICSI for Every Cycle?
The pattern is international rather than local. ESHRE’s Good practice recommendations on add-ons in reproductive medicine (Human Reproduction, 2023) notes plainly that “in some countries or settings, ICSI is used in all couples, irrespective of the results of the fertility work-up”. Several explanations are usually offered, and they are worth separating because they are not equally defensible.
- Avoiding total fertilisation failure. Complete failure of fertilisation after conventional insemination is uncommon but distressing, and ICSI lowers its likelihood. This is a real consideration, but managing an uncommon event by changing the technique for everybody is a trade-off, not a free improvement.
- Laboratory predictability. ICSI produces a more uniform fertilisation timeline, which simplifies scheduling and embryo assessment. That is an operational benefit to the laboratory, not a clinical benefit to the patient.
- Semen quality on the day. A sample can perform worse on the day of retrieval than at the earlier analysis. This is a legitimate reason to decide the technique at the time of the procedure rather than weeks in advance — not a reason for a blanket policy.
- It is billed as an addition. Where ICSI is charged separately, a default preference for it has a commercial dimension. Patients are entitled to know when a recommendation carries that dimension and to ask what the clinical indication is in their own case.
None of these amounts to evidence that ICSI produces more babies in couples with normal semen parameters. They explain a habit; they do not justify it as a universal policy.
Where ICSI Genuinely Helps
The case against routine ICSI is not a case against ICSI. Where sperm cannot fertilise an egg unaided, it is not an enhancement but the entire treatment, and the evidence for it in those settings is not in dispute. NICE NG257 identifies surgically retrieved sperm, frozen–thawed oocytes, abnormal semen parameters graded by severity, and a previous cycle with failed or very low fertilisation. ASRM agrees on the last of these, noting that “ICSI can increase fertilization rates when lower than expected or failed fertilization has previously occurred with conventional insemination”.
One indication used at Wellspring sits outside the NICE list and should be stated openly rather than glossed over. NG257’s ICSI recommendations are framed around conventional semen parameters and do not address sperm DNA integrity. Wellspring’s clinical position, set by Dr. Shah, is that high sperm DNA fragmentation is a recognised indication for ICSI, because a sample can meet standard reference limits while carrying a level of DNA damage associated with poor embryo development and pregnancy loss. Patients should understand both facts: that this indication reflects a clinical judgement about a parameter the guideline does not cover, and that it is applied on the basis of a specific test result rather than as a default.
Where a previous cycle failed at the fertilisation step specifically, changing technique is one of the few genuinely evidence-supported responses — a distinction explored further in our guide to why IVF cycles fail, where fertilisation failure is only one of several possible points of breakdown.
Guideline Positions at a Glance
Source | Year | Position on ICSI without male factor |
|---|---|---|
NICE guideline NG257 | 2026 | “Do not use ICSI for non-male factor fertility problems if the semen parameters are normal.” |
ASRM committee opinion | 2026 | Routine use for all oocytes does not improve live birth rates; no benefit for unexplained infertility, low oocyte yield, diminished ovarian reserve, advanced maternal age or PGT-A. |
Human Reproduction meta-analysis of 6 RCTs | 2026 | No advantage in live birth or cumulative live birth; RR 0.96 (95% CI 0.85–1.09). |
Cochrane review CD001301 | 2023 | Neither method superior for live birth; adverse events probably little or no different. Certainty low to moderate. |
CARTR Plus registry, 140,252 cycles | 2026 | Cumulative live birth 38.5% conventional IVF vs 36.3% ICSI in non-male-factor cycles. |
Questions Worth Asking Before Agreeing to ICSI
- What is the specific indication for ICSI in my case — which semen parameter, which prior result, or which laboratory finding?
- Are my partner’s semen parameters normal against current WHO reference limits? If they are, what is the reason for departing from the guideline position?
- Is the decision being made in advance, or will it be made on the day of egg retrieval based on the sample provided?
- If ICSI is being recommended because of a previous cycle, was the problem specifically at the fertilisation step, or at embryo development, implantation or later?
- Is ICSI charged separately from the base cycle, and would declining it change what is included?
A clinic that is applying the evidence will be able to answer all five without difficulty. Detailed information about the technique itself, its indications and how it is performed at Wellspring is set out on our ICSI treatment page.
Frequently Asked Questions
Is ICSI worth doing if there is no male factor?
Current evidence says no. A 2026 meta-analysis of six randomised trials found live birth rates of 32.8% with ICSI and 34.5% with conventional IVF in couples without severe male factor infertility. NICE guideline NG257 recommends against using ICSI where semen parameters are normal, and ASRM states that routine use of ICSI without male factor does not improve live birth rates.
Does ICSI increase live birth rates in unexplained infertility?
No. ASRM’s 2026 committee opinion states that ICSI in unexplained infertility has been associated with increased fertilisation rates in some studies but has not been shown to improve live birth outcomes. Fertilisation and live birth are different endpoints, and improving the first does not automatically improve the second.
Why do some clinics use ICSI for every cycle?
Reasons given include reducing the risk of total fertilisation failure, more predictable laboratory scheduling, and uncertainty about semen quality on the day of retrieval. Where ICSI is billed separately there is also a commercial dimension. None of these is evidence that ICSI produces more babies in couples with normal semen parameters.
Is ICSI more risky than conventional IVF?
The Cochrane review found that multiple pregnancy, ectopic pregnancy, pre-eclampsia and prematurity showed probably little or no difference between the two techniques, and that clinical pregnancy and miscarriage rates were similarly comparable. The argument against routine ICSI is that it adds cost and intervention without adding benefit, not that it is dangerous.
My semen analysis is normal but we have had a failed fertilisation before. Does that change things?
Yes. A previous cycle with failed or very low fertilisation is one of the recognised indications for ICSI in both NICE NG257 and the ASRM committee opinion, which notes that ICSI can increase fertilisation rates in exactly that situation. This is a different clinical scenario from routine use in a first cycle with normal parameters.
Conclusion
ICSI is indispensable where sperm cannot fertilise an egg on their own, and it is not an upgrade for everyone else. Six randomised trials, a Cochrane review, a registry of more than 140,000 cycles, NICE and ASRM all point the same way: in couples with normal semen parameters, injecting the sperm does not produce more babies. The reasonable expectation of any patient is therefore not that ICSI be avoided, but that it be justified — by a named indication, in their own case, before it is added to their cycle.
Couples who want a second opinion on whether ICSI is indicated in their situation, or who have had a cycle with poor or failed fertilisation, can discuss their individual case with a fertility specialist at Wellspring IVF & Women’s Hospital, Ahmedabad. Call or WhatsApp +91 9099946050. OPD hours are Monday to Saturday, 10:00 AM to 4:00 PM.
References
- National Institute for Health and Care Excellence. Fertility problems: assessment and treatment. NICE guideline NG257. Published 31 March 2026. https://www.nice.org.uk/guidance/ng257/resources/fertility-problems-assessment-and-treatment-pdf-66144022104517
- Practice Committee of the American Society for Reproductive Medicine. Intracytoplasmic sperm injection for nonmale factor indications: a committee opinion (2026). Fertility and Sterility. 2026;126:49–56. https://www.asrm.org/practice-guidance/practice-committee-documents/intracytoplasmic-sperm-injection-for-nonmale-factor-indications-a-committee-opinion-2026/
- Kayimu K, Berntsen S, Fu Y, et al. Does intracytoplasmic sperm injection outperform conventional in vitro fertilization in couples without severe male factor infertility? A systematic review and meta-analysis of randomized controlled trials. Human Reproduction. 2026;41(7):1173–1182. https://academic.oup.com/humrep/article/41/7/1173/8690866
- Cutting E, Horta F, Dang V, van Rumste MME, Mol BWJ. Intracytoplasmic sperm injection versus conventional in vitro fertilisation in couples with males presenting with normal total sperm count and motility. Cochrane Database of Systematic Reviews. 2023, Issue 8. Art. No.: CD001301. https://www.cochrane.org/evidence/CD001301_intracytoplasmic-sperm-injection-versus-conventional-techniques-oocyte-insemination-during-vitro
- Ferraro ZM, Meng L, Liu KE, Greenblatt EM, Russo MA. Intracytoplasmic sperm injection for non-male factor infertility does not improve cumulative live birth rate: a Canadian assisted reproductive technologies registry (CARTR Plus) descriptive study. Frontiers in Reproductive Health. 2026;8:1822305. https://www.frontiersin.org/journals/reproductive-health/articles/10.3389/frph.2026.1822305/full
- ESHRE Add-ons Working Group; Lundin K, Bentzen JG, Bozdag G, et al. Good practice recommendations on add-ons in reproductive medicine. Human Reproduction. 2023;38(11):2062–2104. https://academic.oup.com/humrep/article/38/11/2062/7281712



